
In the webinar below (with a written guide beneath), Dr Sam Kular (interventional radiology fellow) provides a structured approach to CT head interpretation, with an overview of common cases & pitfalls.
Our Webinar
Introduction
As a ward doctor you won’t be writing the formal radiology report, but when you are holding the bleep out of hours you need to spot the big, life-threatening findings yourself so you can escalate quickly. This guide gives you the foundations and a logical, repeatable approach to the key acute pathology.
The basics
Orientation
The patient is lying flat and you are looking from their feet up towards their head. So the right of the image is the patient’s left hemisphere, and the left of the image is their right. The top of the image is the front of the head and the bottom is the back. Flip it in your mind before you start.
Density and windows
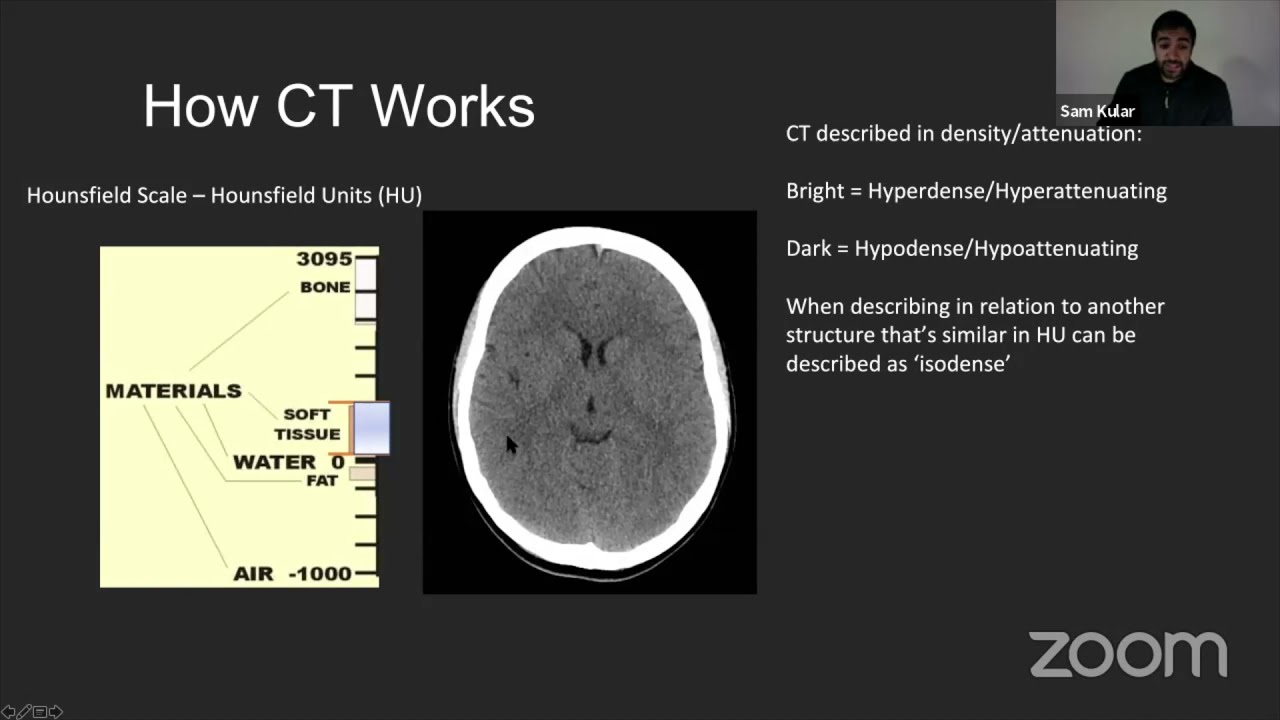
CT uses the Hounsfield scale to measure how much X-ray a tissue absorbs. Air is very dark (around minus 1000), water sits at zero, and dense structures such as bone and metal are bright (into the thousands), with everything else a shade of grey in between. Dark structures are described as low density, hypodense or low attenuation; bright ones as high density or hyperdense.
Because the eye can only separate a limited range of greys at once, the image is set to a ‘window’. Use the soft tissue (brain) window to see grey and white matter, CSF and blood, and switch to the bone window to assess the skull. You will move between the two on every scan.
The layers that matter
Working from the outside in: skull bone, then the dura mater, then the arachnoid mater, then the pia mater, which hugs the brain surface and dips into the sulci. Each type of bleed is defined by which of these planes it sits in, and that is what gives it a characteristic shape.

Figure 1: Meningeal layers – skull, dura, arachnoid, pia over the brain
Requesting a CT head
You have to justify the scan. Current NICE head injury guidance is NG232 (2023), which replaced CG176, and it splits urgency into two groups:
- CT within 1 hour: GCS below 13 on initial assessment (or below 15 at 2 hours), suspected open, depressed or basal skull fracture, post-traumatic seizure, focal neurological deficit, or more than one episode of vomiting.
- CT within 8 hours: some loss of consciousness or amnesia, plus any of age 65 or over, a bleeding or clotting disorder, a dangerous mechanism, or more than 30 minutes of retrograde amnesia.
- Anticoagulation is a standalone 8-hour trigger in its own right, and it means any anticoagulant (including DOACs), not just warfarin.
Ward call tip: when you phone the radiologist, do not just say ‘trauma’. Give the duration of symptoms, the side and specifics of any neurology, and key background such as anticoagulation, cancer or previous strokes. Brain findings localise to specific areas, so a good history tells them exactly where to focus.
Systematic Approach
Blood Can Be Very Bad
Work through the same framework every time: Blood, Cisterns, Brain, Ventricles, Bone. An outside-in approach (skull, then dura, brain, ventricles and cisterns, then soft tissues) works just as well.
Keep the Monro-Kellie doctrine in mind throughout: the skull is a fixed box holding brain, blood and CSF. If any one expands, whether a bleed, hydrocephalus or a mass, the others are squeezed, and the brain has nowhere to go except to shift or herniate.
1. Blood
Blood changes density as it ages, which helps you judge how old a bleed is:
- Acute blood is hyperdense (bright white) for roughly the first week.
- Subacute blood becomes isodense (grey) at about 1 to 2 weeks and blends in with normal brain. This is the easiest to miss, so rely on secondary signs such as mass effect and loss of sulci.
- Chronic blood becomes hypodense (dark) after about two or more weeks. Patients can carry these for years without knowing.
Caveat: hyperacute, unclotted blood can look dark (fluid density) before it clots, so active bleeding may show low density within high density.

Figure 2: Blood density over time – acute hyperdense (bright) vs chronic hypodense subdural (dark)
Then recognise the bleed by its shape and what stops it spreading:
- Extradural (EDH): between the skull and the dura. A biconvex ‘lemon’ or lens shape. The dura is stuck down at the sutures, so the blood cannot cross suture lines, though it can cross the midline.
- Subdural (SDH): between the dura and the arachnoid. A crescent ‘banana’ shape. It crosses suture lines but is stopped at the midline by the falx cerebri, and between compartments by the tentorium.
- Subarachnoid (SAH): between the arachnoid and pia. Blood tracks into the sulci, fissures and basal cisterns, often a star shape centrally. Think trauma, or a ruptured aneurysm (commonly anterior communicating, posterior communicating, or basilar tip).
- Intraparenchymal and contusions: bruising within the brain itself, seen as a focal round bleed. In trauma, look for contrecoup injury. Coup means the same side as the impact and contrecoup the opposite side: the brain slams into the far skull, so the bleed is often opposite the point of impact.


Figure 3: Extradural haemorrhage (left) versus subdural haemorrhage (right)

Figure 4: Subarachnoid haemorrhage
2. Cisterns
Look at the basal cisterns at the base of the brain. They should be dark and full of CSF. If they are squashed flat or missing, suspect raised intracranial pressure and possible herniation. Call for help early.
3. Brain
- Grey-white boundary: loss of grey-white differentiation in a wedge-shaped, low-density arterial territory suggests an ischaemic stroke. The territory helps localise it: ACA (frontal and paramedian), MCA (the large lateral frontal and parietal areas plus the temporal lobe, the biggest territory), and PCA (occipital). Early infarcts are subtle and become clearer over about 24 hours, which is why picking them up early matters for thrombolysis or thrombectomy.
- Cytotoxic versus vasogenic oedema: strokes cause cytotoxic oedema, which swells both grey and white matter. Tumours, abscesses and infections cause vasogenic oedema, which spares the cortex and tracks through the white matter in a finger-like, scalloping pattern.
- Mass effect: watch for effaced ventricles and sulci, midline shift across the falx (subfalcine herniation), or downward transtentorial and tonsillar herniation (coning), which compresses the brainstem and is life-threatening.

Figure 5: Features of ischaemic stroke
4. Ventricles
- The lateral ventricles should be symmetrical dark arches.
- Hydrocephalus: blocked CSF pathways balloon the ventricles and crush the surrounding brain.
- Intraventricular haemorrhage: with the patient supine, acute blood layers in the dependent posterior horns as a bright fluid level. Always check, even for a small amount.
- The choroid trap: do not mistake normal calcified choroid plexus for a bleed. On Hounsfield units, calcium reads in the thousands whereas fresh blood sits at only about 50 to 70, so measure if unsure.
5. Bone
Switch to the bone window to look for fractures.
Fractures versus sutures: sutures are symmetrical zig-zags found on both sides in expected places. Fractures are sharp, unilateral and do not follow those lines. A fracture that runs through a suture and forces it open is called diastasis.


Figure 6: Skull fractures on bone window. Depressed fracture (left), asymmetrical sutural diastasis due to fracture (middle), normal symmetrical sutures (right)
Reading the radiologist’s report
When you scan the typed report, do not overreact to long words that simply describe normal ageing:
- ‘Chronic small vessel disease’, ‘mature ischaemic change’ and ‘periventricular small vessel ischaemia’ are long-standing vascular wear, much like atherosclerosis elsewhere in the body. They are not acute.
- ‘Involutional change’ and ‘generalised cerebral atrophy’ mean age-related shrinkage of the brain.
None of these need any acute action on the ward round. Scan the report for the word ‘acute’: a genuine acute stroke or bleed will be reported as such. If the skull or another structure is not mentioned, it has still been reviewed; it simply means nothing acute was found there.
References
Updated by Dr Haris Hanif (SHO) & Dr Talha Raza (FY1)


2 thoughts on “CT Head Interpretation”
Excellent thank you!
Thank you!