
The advantages of AXRs are far less radiation to patients & that they’re logistically easy to organise out of hours. Unlike CTs they do not need to be discussed with the on-call radiologist but they aren’t reported as quickly therefore it is crucial you can interpret them. The most common indication for an AXR is suspected pneumoperitoneum or obstruction.
Our Webinar
Introduction
Firstly, a quick reminder of the colours of different materials on XR (image from Nottingham University)

Before requesting a scan do check if your patient is pregnant (LMP, recent unprotected sexual intercourse). Although it isn’t an absolute contraindication, it does need discussion with seniors and the duty radiologist to carefully balance the urgency of the scan and potential harm.
The Modern Utility of AXRs
While historically common, the clinical utility of Abdominal X-Rays (AXRs) on the acute take has shifted significantly. According to modern Royal College of Radiologists (RCR) guidelines, an erect Chest X-Ray (CXR) is the first-line investigation for suspected pneumoperitoneum (perforation); it can detect free air under the diaphragm, though CT is more sensitive and is used to confirm and localise the perforation.
Similarly, while an AXR might show dilated loops suggestive of an obstruction, surgical teams will almost invariably require a contrast-enhanced CT Abdomen/Pelvis to definitively identify the transition point and underlying cause. Do not delay definitive CT imaging for an acutely unwell patient by waiting for an AXR.
Systematic Approach
- Identifiers & quality of the film. Projection is usually AP in erect or supine positions
- Air in the abdomen
- Bowels
- Foreign objects and artefacts
- Bones, calcifications & stones (only 10% of gall stones are radio-opaque)
1) Identifiers & quality of the film
- Review that you have the right scan in front of you (date, time and patient’s details)
- Check you can see the entire abdomen (see below)
- Check if right & left are appropriately labelled
- Optimise the exposure so you can see all the structures
- Note any artefacts (piercing, suture clips, lines/tubes)
| Abdominal X-ray | Soft tissue organs and structures of the abdomen | Bony structures of the abdomen |
|---|---|---|
 |  |  |
2) Air in the abdomen
Air rises to the top when there is pneumoperitoneum (e.g. as a consequence of stomach or bowel perforation). But as you can see from the images above, you cannot reliably look for air under the diaphragm in an AXR, which is why an erect CXR is strictly recommended.
Rigler’s sign below demonstrates what a pneumoperitoneum may look like on an AXR. The bowel wall is clearly delineated with black on either side because there is air outside of the bowel. Compare this to the above images.
 |  |
|---|
3) Bowels
Below you can see the radiographic appearances of the normal bowel (compare this to the images above noting that you cannot see black outside of the bowel wall below).


Review the general appearance of the small or large bowel, noting anything that looks unusual. If it looks dilated, use your digital measuring tool to check the diameter. Remember the classic 3-6-9 rule: The small bowel can measure up to 3cm, large bowel up to 6cm (often cited as 5cm for the standard colon), and the caecum up to 9cm.
Small bowel
It is located centrally with circular folds (valvulae conniventes) that the entire width of the bowel. There is normally minimal air from peristalsis. If dilated beyond 3cm, consider small bowel obstruction, which is most commonly caused by adhesions, hernias, or tumours.

Large bowel
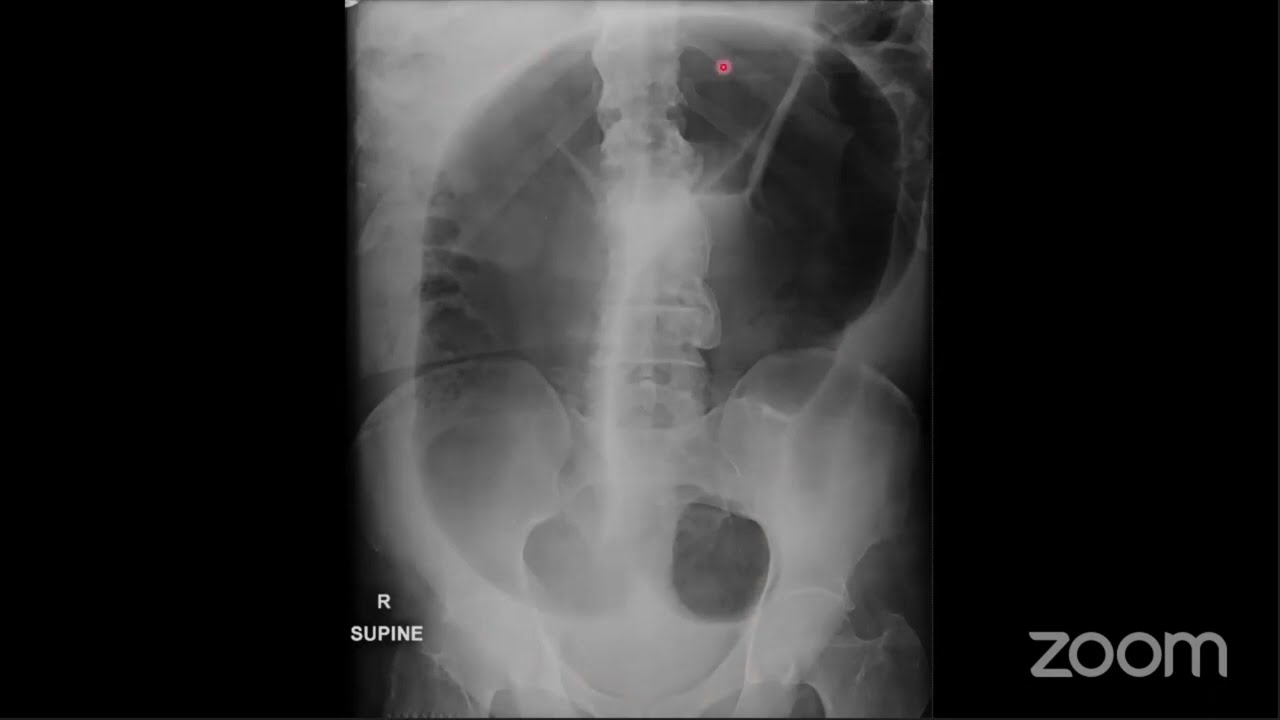
It is peripherally located with incomplete semi-circular folds (haustra) that do not traverse the entire width of the bowel. If dilated beyond normal limits, consider large bowel obstruction, which is most commonly caused by tumours, abscesses, diverticular disease, & volvulus.

Volvulus
A twisting of the bowel is seen as a large pocket of air. It classically appears in a ‘coffee bean’ shape in a sigmoid volvulus, and is ‘kidney’ shaped in a caecal volvulus. The major clinical concern is that the bowel can become ischaemic due to the blood supply cutting off, which is a life-threatening surgical emergency.
| Sigmoid Volvulus | Caecal Volvulus |
|---|---|
 |  |
Ward Trick: A quick way to differentiate the two on a busy shift is to look at the direction the bowel loop is pointing. A sigmoid volvulus typically points up towards the Right Upper Quadrant (RUQ), whereas a caecal volvulus typically points towards the Left Upper Quadrant (LUQ). Remember this is only a heuristic; plain films are often non-diagnostic in volvulus, so confirm with CT.
Spotting faeces
Severe constipation can be demonstrated on an AXR with faecal loading. This appears as hazy clouds, which, if seen in the rectum, demonstrates faecal impaction. This can cause overflow diarrhoea, subacute obstruction, toxic megacolon, and ultimately perforate the bowel.

4) Foreign objects & artefacts
It can be easy to miss objects that have been ingested or inserted if you do not actively look out for them. Similarly, it is easy to miss drains and tubes.
Nasogastric tube (NGT)
According to National Patient Safety Alert (NPSA) guidelines, safe gastric placement of an NGT must first be confirmed by measuring the pH of an aspirate, which must strictly be between 1 and 5.5. It is NEVER appropriate to use the ‘whoosh test’, litmus paper, or the visual appearance of the NG aspirate alone.
If the pH is above 5.5, or if an aspirate cannot be obtained, an X-ray is required. Unless told otherwise by your specific Trust policy, as an FY1 you cannot confirm NG tube placement on an X-ray, as getting this wrong is a “never event” that could result in a patient’s death.
Requesting Tip: When requesting this scan, explicitly ask for an ‘NGT view’ rather than a standard CXR to ensure the radiographer exposes the film adequately to see below the diaphragm.
Reviewing the Film: Ensure the tip of the NGT is clearly visible on the radiograph. If the tube does not follow the midline bisecting the carina, it may be in a bronchus. Ideally, it should extend 10cm beyond the gastro-oesophageal junction. Spotting an incorrectly placed NG tube is critical to ensure it is immediately removed.
Images of a correctly placed NGT are not included purposefully to stress the point that you require separate training. In some places, only a registrar or the radiology team can confirm NGT placement.
5) Bones, calcifications & stones
It is good practice to quickly review the spinous processes looking for scoliosis, fractures, or other bony pathologies. Occasionally you may see kidney or gallbladder stones; however, this is quite rare (only ~10% of gallstones are radio-opaque) and usually, more advanced imaging is required (e.g., a CT KUB for renal stones, or an ultrasound for dilation of the common bile duct).
Resources & References
- Radiology Cafe
- Radiopaedia.org – Abdominal Radiography
- Wikiradiography.net – Featureless films
- Wikiradiography.net – Large Bowel Obstruction
- The Royal College of Radiologists (RCR) – iRefer Guidelines
- NHS England / National Patient Safety Alert (NPSA) – Reducing the harm caused by misplaced nasogastric feeding tubes in adults, children and infants
- NHS Improvement (2016) – Nasogastric tube misplacement: continuing risk of death and severe harm
Written by Dr Alexander Tam (FY1)
Reviewed by Mr Mohammed Abduljabbar (Surgical SpR) & Dr Vivienne Eze (ST4 Radiologist)
Updated by Dr Haris Hanif (SHO) & Dr Talha Raza (FY1)


